
Alopecia in Black Women: CCCA, Traction Alopecia Signs, and the Treatment Landscape
CCCA alopecia in Black women, the treatment landscape exactly as the dermatology literature describes it, and the traction alopecia signs that tend to arrive first — an honest map, in general information only.
The questions tend to arrive in a particular order. First, the crown feels thinner under the hand than it used to. Then a part that seems wider in photographs than in the mirror.
Then tenderness, or an itch that styling products do not settle, in exactly the place where the hair is changing. And then, usually late at night, the search itself — ccca alopecia black women treatment traction alopecia signs — typed by a woman who has decided she would rather know than wonder. This article is written for that moment.
It is a map of what the clinical and dermatological literature says about hair loss in Black women: the forms that appear most often in that literature, the patterns by which they are recognised, what a dermatologist's examination involves, and the treatment landscape as specialists describe it. It is general information, drawn from named sources and attributed throughout.
It is not advice for any one head, and it does not pretend to be.
One thing the literature is clear about is scale. Survey research presented at an American Academy of Dermatology annual meeting, and reported under the headline that almost half of African-American women have experienced hair loss, describes a problem that specialists at that meeting characterised as widespread and often undiagnosed.
The dermatologist quoted in that reporting, Dr. Yolanda M. Lenzy, identified central centrifugal cicatricial alopecia — CCCA — as the leading cause she sees in this population, with traction alopecia close behind and female pattern hair loss also in the picture. A map, then, is not a luxury.
For a readership that handles every other part of life with information and excellent professionals, the scalp deserves the same standard.
Why an Honest Map Matters
Hair, in this community, is never only hair, and the researchers who study its loss say so in plain language. Reporting on a Johns Hopkins review of the traction alopecia literature carried the words of dermatologist Dr. Crystal Aguh:
Hair is a cornerstone of self-esteem and identity for many people.— Dr. Crystal Aguh, Johns Hopkins University School of Medicine, via ScienceDaily
That sentence explains both halves of the problem this article maps.
It explains why hair loss carries a weight out of proportion to any single strand — and it explains the irony the same researchers underline: that some hairstyles meant to improve self-confidence can lead to hair and scalp damage when tension, weight, heat and chemistry are allowed to accumulate on the follicle for years.
An honest map holds both truths at once. Nothing in the pages that follow is an argument against braids, weaves, silk presses or any other element of the repertoire. The literature does not make that argument either.
What it maps is mechanism — what pulls, what inflames, what scars — so that the choices around styling and treatment are informed ones, made early, while the most options remain open.
Timing is the second reason for honesty. Several of the conditions described here are, in the literature's own framing, races against scarring. Where a follicle is inflamed but alive, the treatment conversation is about calming and preserving.
Where scarring has replaced the follicle, the conversation changes entirely, because scarred skin does not regrow hair. That is why specialists return, in source after source, to the same theme: signs recognised early are options preserved.
The map below is organised in that spirit — the centre of the picture first, then the edges, then the visit, then the landscape of what medicine currently offers.
CCCA: The Centre of the Map
Central centrifugal cicatricial alopecia is, in the words of the peer-reviewed review literature, the most common scarring alopecia among African American women. Dermatology practice sources describe it the same way from the clinic side: a scarring form of alopecia in which follicles are destroyed and the loss becomes permanent, seen predominantly in middle-aged Black women. Its name is its pattern.
The loss begins at the crown, the centre of the scalp, and expands outward in a gradually widening circle — central, centrifugal — leaving, in advanced descriptions, smooth and shiny skin where follicle openings once were.
How common is it? The American Academy of Dermatology's reporting, quoting Howard University dermatologist Dr. Valerie D. Callender, puts the estimate at nearly 15% of Black women — a figure that makes CCCA, in that reporting, the most common type of hair loss seen in women with darker skin tones.
What causes it is the honest unknown at the centre of the map. Practice sources state plainly that its cause is not established, with genetics and hair-care practices both postulated in the literature.
The review literature adds texture to the genetics side: in a small series, CCCA has been shown to be inherited in a pattern consistent with autosomal dominant transmission, with hairstyling and sex described as strong modifying effects — which is a careful way of saying that inheritance may load the follicle, and practice may pull the trigger, and neither alone tells the whole story.
Any source that claims a single, settled cause for CCCA is ahead of its evidence.
The symptoms, as clinical references catalogue them, are often quiet at first. References on the condition list thinning or bald patches at the crown; tenderness, itching or burning; and, in some cases, redness or scaling. That quietness is the trap.
Itching and scaling are easily filed under dandruff; tenderness is easily blamed on a recent style. Meanwhile the defining feature of a cicatricial — scarring — alopecia is progressive: inflammation at the follicle, then fibrosis, then a follicle that no longer exists.
The literature's consistent counsel, reflected in the AAD's reporting, is that early detection matters precisely because the sequence can be interrupted early and cannot be reversed late.
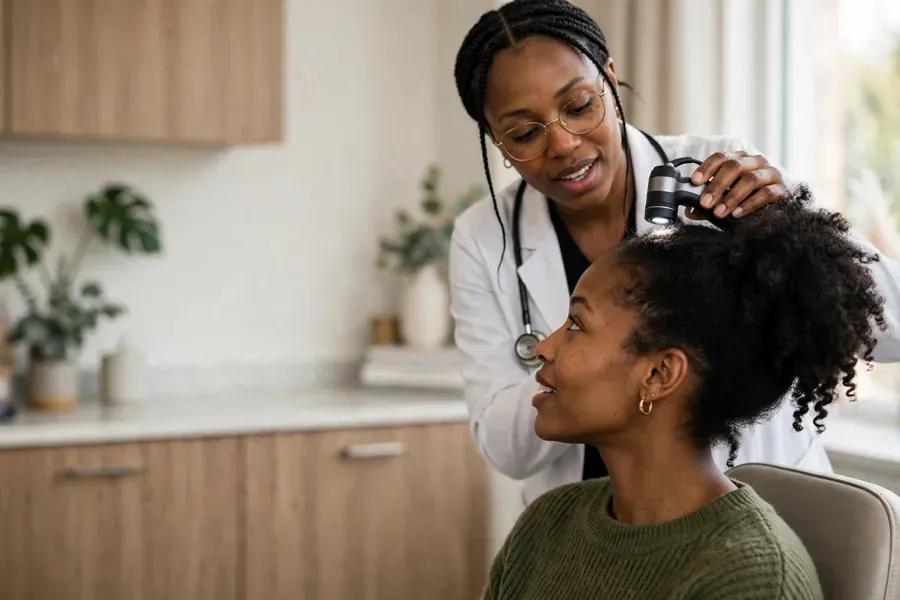
Traction Alopecia: The Form With a Mechanism
If CCCA is the map's mystery, traction alopecia is its mechanics. The Johns Hopkins review — an analysis of 19 studies published in the Journal of the American Academy of Dermatology — reports what its authors call a strong association between scalp-pulling styles and traction alopecia — the gradual loss that builds when follicles are kept under prolonged, repeated tension.
The same reporting carries the review's estimate that one-third of African-American women experience this form of loss, which would make it the most common form in that group overall.
The styles the researchers categorised as highest-risk share a recipe: tension plus weight plus duration, with braids, dreadlocks, weaves and extensions named — especially, the review notes, when applied to chemically treated hair.
The signs, in the American Academy of Dermatology guidance summarised by public-radio science reporting, are specific enough to learn by heart: broken hairs along the forehead, a hairline that recedes, and patchy loss exactly where styles pull tightest. Dermatology coverage adds the sensory sign that precedes the visible ones.
Dr. Callender, in reporting on hair-loss comorbidities, puts it as a sentence worth embroidering:
Getting your hair done shouldn’t hurt, so if they have pain, it’s an indicator that they could be developing traction alopecia.— Dr. Valerie Callender, via Dermatology Times
Pain, in other words, is data. So are the small bumps around follicles, the tenderness at the hairline in the days after an install, and the soreness that has been normalised in salon folklore as the price of a style that lasts. The literature does not treat it as a price.
It treats it as an early sign — and early is the operative word, because the Johns Hopkins researchers describe traction alopecia as preventable in the researchers' assessment, and reversible when the tension is caught and removed early.
The mechanism that makes it dangerous over years is the same one that makes it addressable early: remove the tension while the follicle is strained but intact, and the story can change. Leave the tension in place across years of installs, and strained follicles can scar — at which point traction loss joins the permanent category.
The Other Names on the Map
CCCA and traction alopecia are the centre of this map because the slate of this article — and the epidemiology — puts them there, but they are not the whole territory, and an honest map says so.
Female pattern hair loss, hereditary in nature, appears throughout the same literature: dermatology reporting notes that it affects millions of women, with minoxidil among the treatments commonly discussed for it — a different mechanism from either scarring or tension, and one reason a thinning crown cannot be self-diagnosed from a mirror.
The same body of reporting records that the conditions travel with company: Dr. Callender's AAD presentation described women experiencing hair loss as also presenting, in notable numbers, with conditions such as diabetes, acne and high blood pressure — associations the AAD frames as a reason the dermatology visit can surface more than a scalp finding.
Overlap is the other complication the literature insists on. A scalp can carry more than one process at once — traction at the hairline, pattern loss at the part, early CCCA at the crown — and clinical references note that establishing which process is present, and where, is exactly what the diagnostic examination is for.
References describe dermoscopy helping the clinician choose the best biopsy site, with the biopsy itself establishing the diagnosis, and biopsy material being examined for the fibrosis and inflammation patterns that distinguish one scarring process from another. The point for the reader of this map is not to memorise the taxonomy.
It is to understand why specialists resist naming a condition from a photograph, and why the visit described next exists at all.
The Dermatologist Visit, as the Literature Describes It
Assembled from the clinical references, a thorough evaluation for hair loss of this kind has recognisable components. There is the clinical examination itself — scalp, pattern, and the history of styling and symptoms around it. There is dermoscopy, the non-invasive magnified examination of scalp and follicles that references describe as part of differentiating CCCA from other forms of loss.
There may be a scalp biopsy, which the same references describe as the step that confirm scarring and inflammation, and separate CCCA from the other conditions it can resemble. And there may be blood tests, described in those references as a way to rule out other conditions that produce similar symptoms. None of this is exotic.
It is the standard architecture of a diagnosis made carefully, in a field where several different conditions can wear the same first symptom.
Why the insistence on precision? Because the treatment landscape divides along diagnostic lines, and because one widely repeated figure from the AAD's reporting reframes the visit entirely:
By recognizing the signs of hair loss and seeing your dermatologist as soon as possible, you may be able to limit the progression, hold on to the hair you have, and discover any other underlying medical conditions you may have.— Dr. Valerie D. Callender, via the American Academy of Dermatology
Hold on to the hair you have — that is the literature's own summary of the goal, and it is a more honest promise than regrowth rhetoric. In scarring alopecia, preservation is the prize, and preservation is a function of timing.
The Treatment Landscape, Without the Salesmanship
Here is the landscape as the sources describe it, with the limits stated as plainly as the options. For CCCA, practice and review sources agree there is no cure; the aim of treatment is to halt progression and manage symptoms.
The review literature names the classes clinicians draw on: minoxidil, calcineurin inhibitors, and steroids given topically or by intralesional injection, described as potentially helpful in slowing progression, alongside the standing counsel to avoid traction and chemical treatments while the scalp is being treated.
Practice sources fill in the same shelf from the clinic side — topical medications, intralesional steroid injections, and oral medications such as antibiotics and antimalarials among the therapies that have been tried — with the discontinuation of traumatic hair practices described as highly encouraged.
A secondary overview of the landscape adds that minoxidil is described as an adjunct supporting growth from remaining viable follicles rather than a stand-alone answer for CCCA, and that transplantation enters the conversation, where it enters at all, only once the disease has been quiet and controlled for an extended period.
Read that landscape carefully and its shape becomes clear. Every element of it is clinician-directed. Steroids, intralesional injections, systemic anti-inflammatory medicines — these are prescription instruments, dosed and sequenced by the physician who has seen the scalp, read the biopsy, and knows which process is active.
Nothing in the reputable literature describes a product shelf that substitutes for that judgement, and this article will not invent one. What general information can honestly offer is the framework: in scarring disease, treatment targets inflammation and progression; in traction disease, treatment begins with removing the mechanical cause; in pattern loss, the commonly discussed options are different again.
The framework is the map. The route across it belongs to the clinician in the room.
Styling While Healing, and the Wig as Bridge
The styling chapter of the literature is continuous with its treatment chapter: the same sources that describe therapy describe practice.
The review literature's patient counsel is to avoid traction and chemical treatments; dermatologist writing on protective styling fills in what lower-tension practice looks like — a wig worn over loosely braided or flat-wrapped hair, secured without pulling, is described as among the lower-tension options, while adhesives, tight elastic bands and combs are flagged as potential irritants at the hairline.
The distinction the literature keeps making is not between styles that are approved and styles that are forbidden. It is between tension and its absence — between an install the scalp protests and one it tolerates, between back-to-back installs with no interval and a rotation that gives follicles rest.
That distinction is what makes the wig, in this literature, a bridge rather than a surrender. A well-made unit, worn over hair that is rested, loose and cared for, carries the public presentation — the gala, the boardroom, the photograph — while the scalp underneath is left alone to be treated.
It is the same logic this magazine applies everywhere else: the standard is not lowered; it is relocated, from endurance to strategy. The woman who understands the map does not have to choose between looking like herself and keeping her hair. She sequences.
Treatment and rest underneath; polish on top; and a stylist who is treated as a partner in the plan rather than an adversary of it — told what the dermatologist has said, and enlisted in keeping tension out of the rotation.
A closing word, in the spirit the whole map was drawn in. Everything here is general information from named clinical and dermatological sources — what the literature says about causes it has and has not established, patterns it recognises, and a treatment landscape it describes with unusual candour about its own limits.
It is not a diagnosis, and it is not a prescription. For the diagnosis and the prescription, the literature points, in every source this article drew on, to the same address: a board-certified dermatologist — ideally, in this magazine's standing counsel, a dermatologist who knows Black skin, Black hair, and the difference between the two kinds of attention both deserve.
The Skin We're In: Hyperpigmentation, Melanin Experts, and the Dermatologist Who Gets It
Weaves and Wigs, Done Right: The Invisible Install
Black Hair for Women: The Care Beneath the Style
Hair as Signature
Cocoa Butter and Shea Butter: The Real Grades, the Real Rituals
Women — Black Excellence Profiles
American Academy of Dermatology — "Research suggests connection between hair loss in women and other diseases"
Commonwealth Dermatology — "Central Centrifugal Cicatricial Alopecia"
Clinical, Cosmetic and Investigational Dermatology (PMC) — "Central centrifugal cicatricial alopecia: challenges and solutions"
Symptoma — "Central Centrifugal Cicatricial Alopecia (CCCA): Symptoms, Diagnosis and Treatment"
ScienceDaily — "All hairstyles are not created equal: Scalp-pulling and hair loss" (Johns Hopkins review)
ScienceDaily — "Survey: Almost half of African-American women have experienced hair loss"
Dermatology Times — "Comorbidities Women With Hair Loss May Experience"
A Moment of Science (IPM) — "Some hairstyles can lead to traction alopecia"
Dina Strachan, MD — "Do Protective Hairstyles Cause Hair Loss?"
Hair Health Blog — "Central Centrifugal Cicatricial Alopecia (CCCA)"
Questions & Answers
Who will you meet on this page?
CCCA alopecia in Black women, the treatment landscape exactly as the dermatology literature describes it, and the traction alopecia signs that tend to arrive first — an honest map, in general information only. It links to 6 stories and articles — open any card to read the full piece.
What makes these stories worth reading?
CCCA alopecia in Black women, the treatment landscape exactly as the dermatology literature describes it, and the traction alopecia signs that tend to arrive first — an honest map, in general information only.
How do I read the full stories on Alopecia in Black Women: CCCA, Traction Alopecia Signs, and the Treatment Landscape?
Choose any card on this page. Each one opens a full page of its own — the complete story or article, with its sources linked.